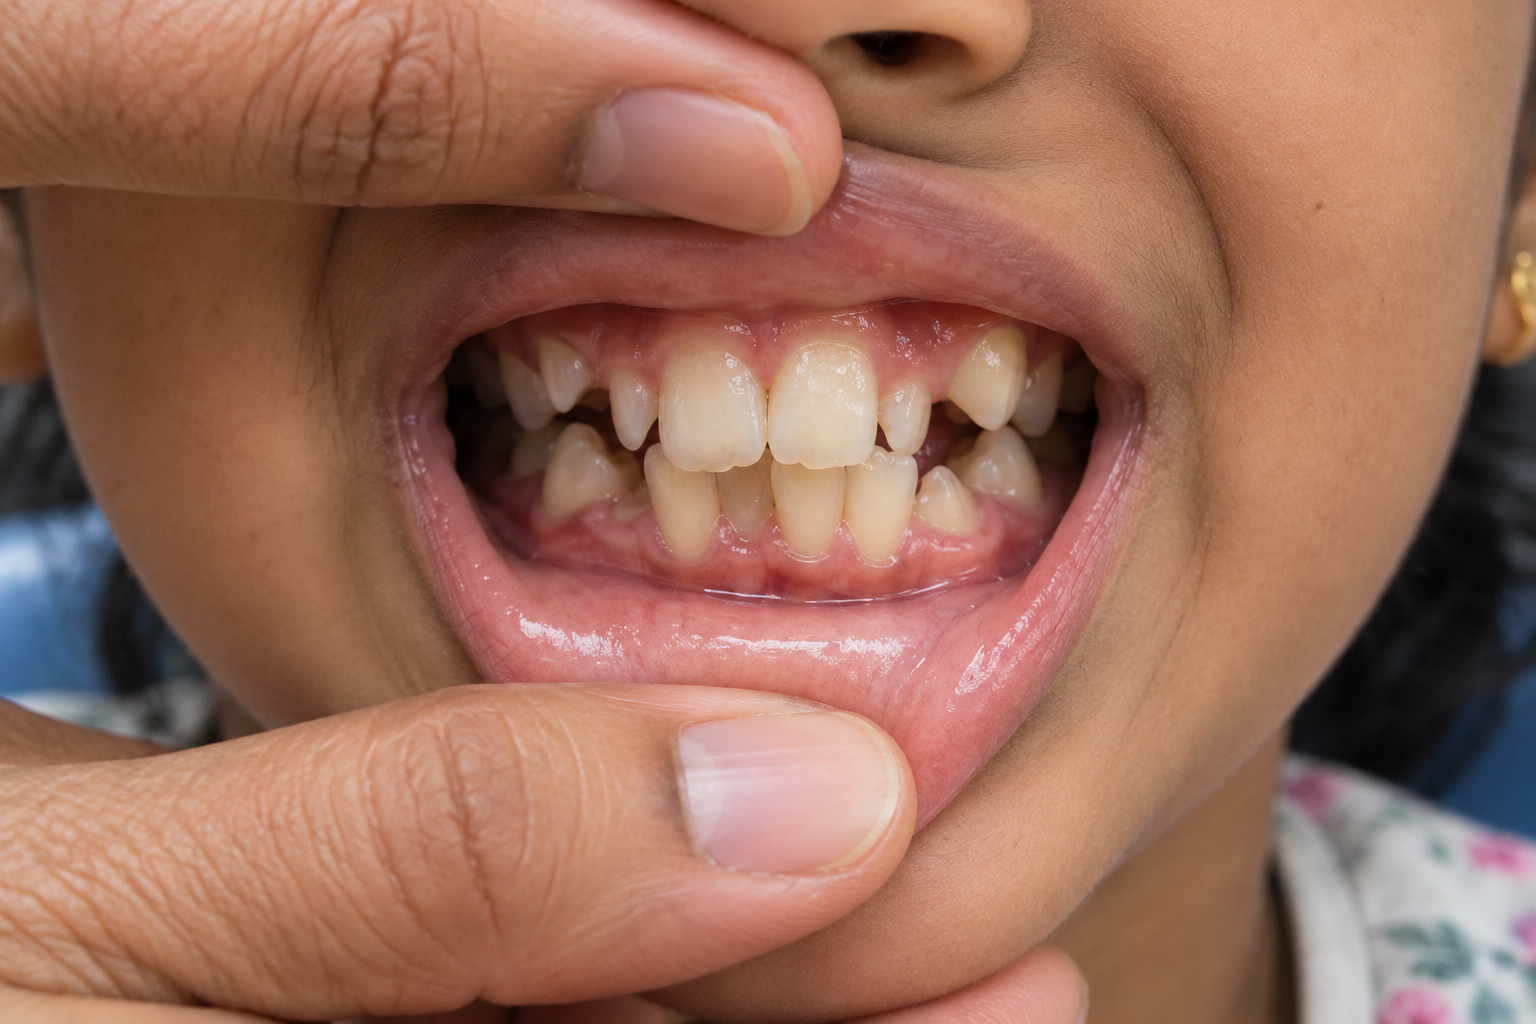
Why Do Children's Teeth Come In Crooked?
Crooked teeth rarely happen by chance. Most malocclusion has an identifiable cause — and many causes are addressable, especially when caught early.
- GeneticsJaw size and tooth size are inherited separately. A child can inherit a small jaw from one parent and large teeth from the other.
- Early loss of baby teethLosing a baby tooth too early allows neighbouring teeth to drift into the space, reducing room for the permanent tooth.
- Prolonged oral habitsThumb sucking, dummy use, and mouth breathing alter the shape of the developing jaw over time.
- Tongue tieA restricted tongue sits low in the mouth instead of resting on the palate, preventing the upper jaw from expanding normally.
- Soft dietModern diets with minimal chewing do not provide sufficient stimulation for jaw development.
- Nasal obstructionChildren who cannot breathe through their nose develop narrower upper jaws and characteristic facial changes over time.
Both the Indian Association of Paediatric Dentistry (IAPD) and the American Association of Orthodontists (AAO) recommend a first orthodontic assessment by age 7 — not because treatment always starts then, but because developing problems are most visible on X-ray at this age and intervention is most effective. Many parents wait until all permanent teeth have erupted — by which point the optimal growth window has passed.
Age-by-Age Treatment Guide
Age 5–7: Early Assessment
We look at jaw width, bite relationship, spacing, and facial growth pattern. Most children at this age need monitoring only — but a crossbite, significantly protruding upper jaw, or severe crowding are worth addressing early.
Age 7–10: Interceptive (Phase 1) Treatment
If we identify a jaw discrepancy — a narrow upper jaw, a crossbite, or significant overbite — early intervention with a removable or fixed appliance can guide jaw growth before it is complete. This often reduces or eliminates the need for extractions or complex fixed braces later.
Age 9–13: Active Orthodontic Treatment
The most common window for comprehensive orthodontic treatment. Most or all permanent teeth have erupted and the jaw is still growing. Braces or aligners at this stage take full advantage of remaining growth. Treatment typically lasts 18–24 months.
Age 14–18: Teen Orthodontics
For teens who missed early intervention, comprehensive orthodontics remains very effective. Clear aligners are a popular option for older teenagers. Some cases not intercepted early may require tooth extraction to create space — which is why we encourage earlier assessment.
Orthodontic Options at Dr. Mittal's
Myofunctional Appliances
Removable appliances worn for several hours daily that guide jaw growth, retrain muscle function, and correct breathing patterns. Most effective between ages 6–10. These address the cause of malocclusion, not just the teeth.
Rapid Maxillary Expansion (RME)
A fixed appliance that gently widens the upper jaw over 2–4 weeks. Used for crossbites and narrow upper jaws. Most effective before age 13. Results are stable and permanent.
Space Maintainers
Custom-fitted appliances placed after early tooth loss to hold space for the incoming permanent tooth and prevent crowding. Simple, comfortable, and highly effective at preventing a much bigger problem later.
Metal, Ceramic & Self-Ligating Braces
Fixed braces remain the most precise and reliable orthodontic treatment for comprehensive cases. We offer metal (most durable), ceramic (tooth-coloured), and self-ligating (lower friction) options. Treatment typically 12–24 months.
Clear Aligners
A series of custom-made clear removable trays that gradually move teeth. Ideal for teens and young adults with mild to moderate crowding who want a near-invisible option. Requires discipline — 20–22 hours of wear per day.
Retainers
All orthodontic treatment must be followed by a retention phase. We provide custom-fitted fixed or removable retainers to maintain corrected tooth position for life. Skipping retention is the most common reason teeth relapse.
What Parents Say
“We brought our daughter at 8 after noticing crowding. Dr. Mittal explained exactly why treatment at this age would prevent something much more complex later. Two years on, her alignment is perfect and she never needed a tooth extracted.”
“My son’s teeth were noticeably crooked and his jaw looked narrow. The palate expander widened his arch and created space naturally — no extractions needed. The team was transparent about every step of the process.”
“I was told to wait until all permanent teeth came in. Dr. Mittal explained that waiting would mean a far longer and more expensive treatment. Starting Phase 1 early was the right call — we are seeing results ahead of schedule.”
Frequently Asked Questions
Yes — this is one of the most common and overlooked causes. Chronic mouth breathing changes tongue posture, reduces the natural pressure that guides teeth into correct alignment, and often causes a narrow palate. Addressing the breathing pattern early — through myofunctional therapy or ENT evaluation — can significantly reduce the complexity of any orthodontic treatment needed later.
It depends on the underlying cause. Phase 1 (interceptive) treatment around ages 7–9 is used for jaw-width problems, severe crowding, or crossbites where early action changes the jaw’s growth path. Phase 2 comprehensive treatment starts after all permanent teeth erupt, usually ages 11–13. Starting at the right time for the right reason matters more than any specific target age.
Untreated crowding and alignment issues tend to worsen with jaw growth. Crowded teeth are harder to clean, increasing cavity and gum disease risk. Crossbites and overbites affect chewing mechanics and, in some cases, jaw joint health. Orthodontic treatment is faster, simpler, and less expensive when done during the growth years. Adult orthodontics is effective but takes longer and typically costs more.
Usually both. Genetics determines jaw and tooth sizes — if they don’t match, crowding results. Habits — prolonged thumb sucking, mouth breathing, tongue thrusting — can independently push teeth out of alignment. In many children, both factors operate together. An orthodontic assessment identifies the primary driver so treatment addresses causes, not just appearance.