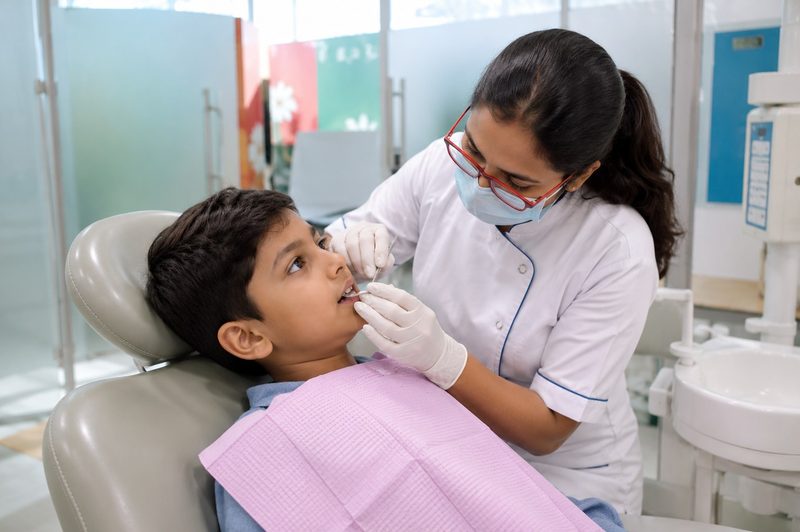
When decay is caught early, a small tooth-coloured filling restores the tooth completely. We remove only what is diseased — preserving every milligram of healthy tooth structure — and your child eats normally the same day. The goal is always to do the least that achieves the most.
Why Baby Teeth Need Fillings
The most common reason parents hesitate is: "It's just a baby tooth — it will fall out anyway." This is understandable, but it misses something important. Baby molars stay until age 10 to 12. A cavity today means pain, infection, and potential damage to the permanent tooth forming beneath — often within months of detection.
Children's enamel is thinner and softer than adults'. A cavity that looks small on the surface can reach the nerve within 6 to 12 months. Once it does, a simple filling becomes a pulpotomy (baby root canal) or extraction.
- Baby teeth hold space — when a back baby tooth is lost early, the neighbouring teeth drift in. This blocks the permanent tooth and creates crowding that often needs braces to correct.
- Chewing matters for nutrition — children with toothaches avoid hard foods and eat selectively, affecting nutrition and growth.
- Chronic low-grade infection — an abscessed baby tooth is a constant source of bacteria, linked to more frequent illness and, in severe cases, spread of infection to the jaw bone.
What We Use and Why
Composite Resin (Tooth-Coloured Filling)
The same material used in adult teeth. Bonds directly to the tooth — no need to shape a cavity. Used for front teeth and visible areas where aesthetics matter. Requires a dry field, so best for cooperative children aged 4 and above.
Glass Ionomer Cement (GIC)
A fluoride-releasing material that bonds to both tooth structure and moisture. Excellent for very young children (under 3) where dryness is difficult to maintain, and for teeth close to shedding. GIC releases fluoride continuously, protecting the surrounding tooth structure.
Resin-Modified GIC (RMGIC)
Combines the moisture tolerance of GIC with better aesthetics. Our most commonly used material for the back baby teeth — a balance of durability, fluoride release, and appearance.
Choosing the Right Treatment: SDF, GIC, Composite & MID
| Treatment | Best For | No Drill? | Cavity Arrest |
|---|---|---|---|
| SDF (Silver Diamine Fluoride) | Very young or anxious children; active cavities in baby teeth; delaying until cooperation improves | Yes — applied in 30 seconds | Yes (turns cavity black) |
| GIC (Glass Ionomer Cement) | Baby molars, young children, moist conditions; releases fluoride throughout life of filling | Minimal drilling only | Partial (fluoride release) |
| Composite (tooth-coloured) | Larger cavities, front teeth, cooperative children; strongest aesthetics and durability | Minimal with MID technique | No (restores, does not arrest) |
| MID Approach | Any cavity where preserving healthy tooth structure is the priority; uses air abrasion or laser for minimal tissue removal | Often yes (hand instrument / laser) | Combined with GIC or composite |
Child under 4 or severe anxiety? → SDF first — no drill, no injection.
Cooperative child, moderate cavity? → MID composite or GIC.
Large cavity at risk of fracture? → Consider stainless steel crown (SSC).
Multiple teeth, cannot cooperate? → Full rehabilitation under general anaesthesia.
We will always discuss your options at the appointment and let you choose with full information.
Minimally Invasive Dentistry (MID)
MID means removing only diseased tissue — no more. Where traditional dentistry sometimes drilled large cavities for mechanical retention, we now bond to the tooth. Adhesive materials hold without needing the tooth to be shaped like a box.
- Caries detection dye — a pink dye shows exactly which dentine is infected versus just softened. We stop removing tissue the moment the stain clears.
- Silver Diamine Fluoride (SDF) — for very young children, anxious children, or cavities in baby teeth near their natural shedding time, SDF arrests the cavity without any drilling. Applied in one minute. No injection. The treated area turns black, which parents are counselled about in advance.
- Indirect pulp capping — when decay is very deep but the nerve is not yet exposed, we place a medicated base layer to protect the nerve and seal the cavity. This often avoids the need for a pulpotomy entirely.
What to Expect at the Appointment
- Tell-Show-Do introduction — we show your child every instrument before using it and explain what each step will feel like, using child-friendly language.
- Topical anaesthetic — a numbing gel is applied to the gum for 2 minutes before any injection, so they feel pressure but not the needle.
- Local anaesthetic — the area is completely numb before we touch the tooth. We wait until your child confirms they cannot feel it.
- Decay removal — only infected tissue is removed, guided by caries detection dye where needed.
- Filling placement — the material is placed, shaped, and hardened with a curing light.
- Bite check — we adjust until the bite feels completely natural.
What Parents Say
“My 5-year-old needed fillings on two teeth. I was dreading it, but with the numbing gel first she barely reacted. She left holding a sticker and asked when we could come back. I was genuinely amazed.”
“The composite filling matched the tooth colour perfectly — you honestly can’t tell it’s there. The procedure was quick, my son was calm throughout, and the team was completely upfront about every step.”
“My daughter had four cavities. We did two per visit. Both appointments were handled beautifully — she was distracted with cartoons, numbing gel went in first, and there were no tears at all.”
Frequently Asked Questions
GIC (glass ionomer cement) is tooth-coloured, releases fluoride, and bonds without needing the tooth fully dry — ideal for very young or anxious children and baby molars. Composite (resin) is stronger and more aesthetically precise, better for larger cavities and front teeth. We choose based on cavity size, tooth type, the child’s age and cooperation, and how long the tooth is expected to remain.
GIC fillings in baby teeth last 3 to 5 years on average. Composite fillings can last 5 to 7 years. Since most baby molars naturally shed between ages 10 and 12, a filling placed at age 5–6 is designed to outlast the tooth. We assess filling integrity at every check-up and repair or replace if wear or recurrent decay is detected before natural shedding.
Related treatments: