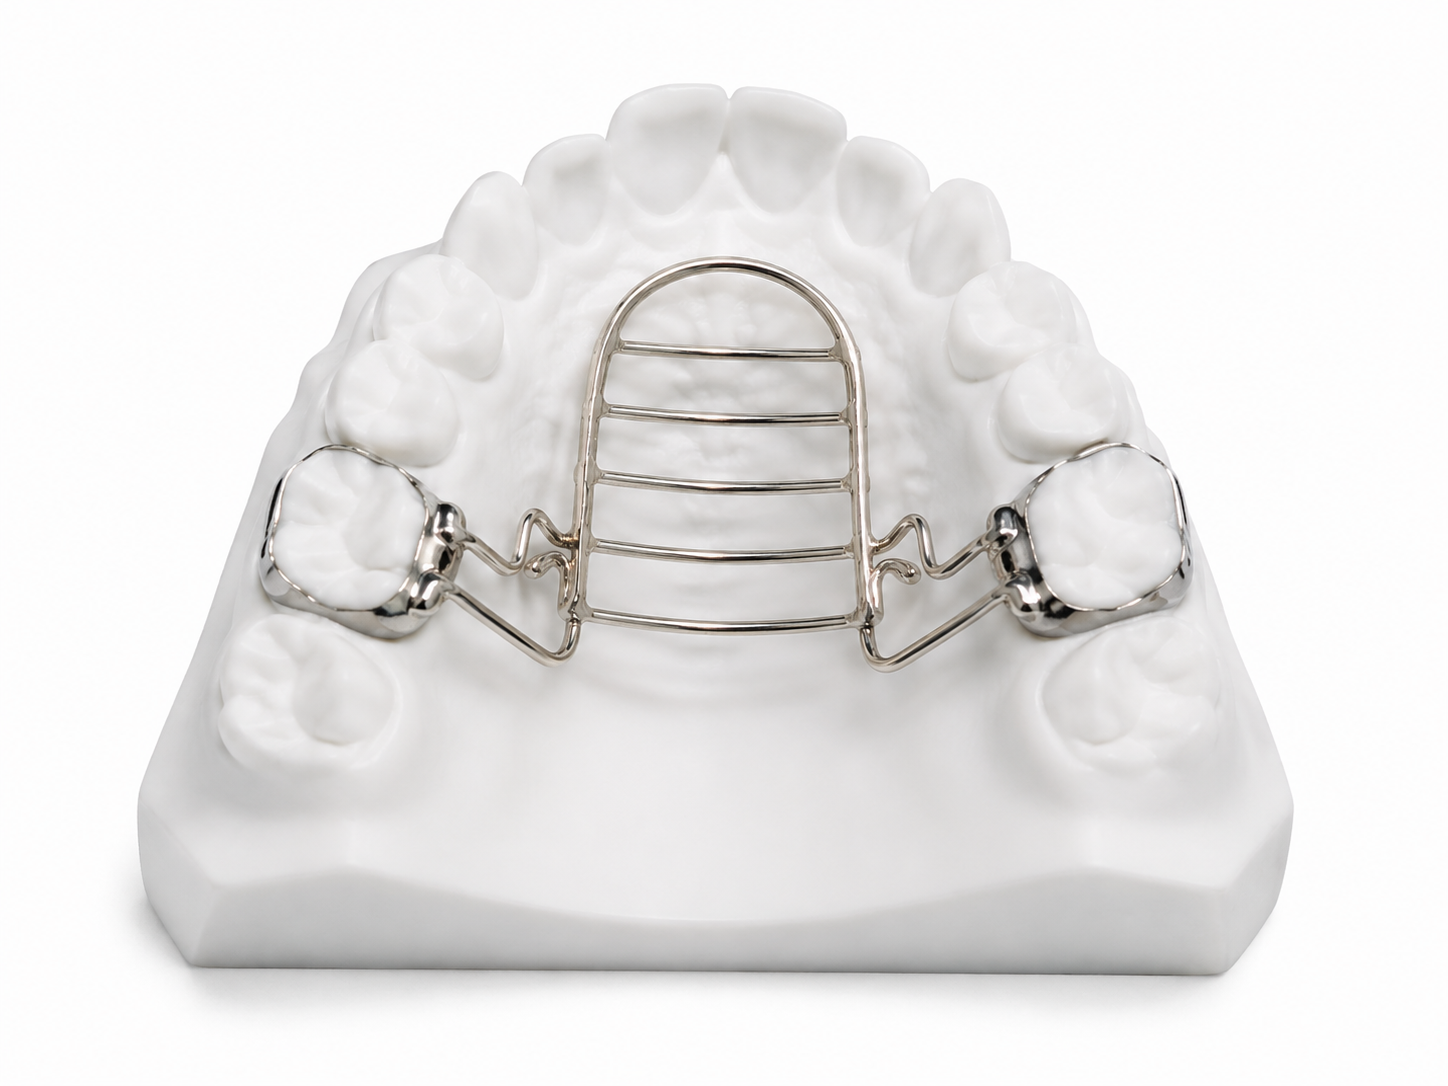
What Are Myofunctional Appliances?
Myofunctional (or functional) orthopaedic appliances are removable devices that work by repositioning the mandible (lower jaw) and using the stretch of the muscles and soft tissues to stimulate bone growth and remodelling. They do not move individual teeth — they guide the jaws.
This makes them most effective during the active growth period (roughly ages 6–12 in girls, 6–14 in boys) when the jaw joints and bone are most responsive. The "growth window" closes as puberty ends, which is why the timing of referral matters so much.
Types of Myofunctional Appliances
Twin Block Appliance
The most widely used functional appliance for treating Class II malocclusion (the lower jaw is behind the upper jaw, creating a significant overjet). Two acrylic blocks — one upper and one lower — engage each other at an angle when the child closes, guiding the lower jaw forward with each bite. Worn full-time except for sports and cleaning. Typically used for 9–12 months.
Bionator
A single removable appliance worn in the mouth that repositions the mandible forward and holds it in an advanced position. Slightly less bulky than the Twin Block. Often used as a follow-up to initial treatment. Worn at night and as many daytime hours as possible.
Activator
One of the original functional appliances. A single bulkier acrylic device worn primarily at night. Less frequently used today but still indicated in certain jaw discrepancy patterns.
Rapid Maxillary Expansion (RME)
The upper jaw (maxilla) is formed by two halves joined at the midpalatal suture. In children and young adolescents, this suture is still open — meaning it can be physically widened by applying gradual lateral force. This is what RME does.
How It Works
A fixed expander is bonded to the upper back teeth. A small key is used to turn a central screw once or twice daily. Each turn widens the appliance by 0.25 mm, applying gentle pressure that gradually separates the two halves of the palate. Over 3–4 months, a significant increase in upper arch width is achieved. The suture then fills in with new bone during a 4–6 month retention phase.
What RME Achieves
- Widens the upper arch to match the lower — correcting posterior crossbite
- Creates space for crowded teeth, reducing or eliminating the need for extraction
- Expands the nasal floor, increasing nasal cavity volume by 30–50% — significantly improving nasal breathing in mouth-breathing children
- Improves tongue posture by providing a wider shelf for the tongue to rest on
When Must RME Be Done?
RME is ideally performed between ages 7 and 12, before the midpalatal suture begins to fuse. In girls, fusion typically begins around age 13–14; in boys, somewhat later. RME after fusion requires much higher forces and is significantly less effective without surgical assistance (SARPE — surgically assisted rapid palatal expansion).
Myofunctional Appliances vs Fixed Braces
| Myofunctional Appliance | Fixed Braces (Phase 2) | |
|---|---|---|
| What it moves | Jaws and bones (orthopaedic) | Individual teeth (orthodontic) |
| Best age | 6 – 12 years (active growth) | 11 – 14 years (all permanent teeth present) |
| Removable? | Yes (except RME, which is fixed) | No — bonded to teeth |
| Reduces need for extractions? | Often yes — by creating space in the arch | May require extraction in severe crowding |
| Used together? | Yes — Phase 1 (myofunctional) often followed by Phase 2 (braces) for best combined result | |
Myofunctional Therapy Goals
| Function | Target Behaviour | Why It Matters |
|---|---|---|
| Tongue posture | Tongue resting on the palate, not the floor of the mouth | Tongue pressure shapes the upper jaw; correct posture guides proper arch width |
| Lip seal | Lips closed at rest without muscular strain | Closed lips force nasal breathing; open lips allow mouth breathing to become habitual |
| Nasal breathing | Breathing exclusively through the nose at rest and during sleep | Nasal air is filtered, humidified and warmed; mouth breathing is a driver of narrow arches and sleep disruption |
| Swallowing pattern | Tongue tip touches palate behind upper teeth (not between teeth) during swallow | Tongue-thrust swallowing pushes the front teeth forward; correct pattern prevents relapse after orthodontics |
Age-Based Intervention Guide
| Age | Typical Concern | Preferred Appliance / Approach |
|---|---|---|
| 6 – 8 years | Narrow upper arch, posterior crossbite, mouth breathing | RME (Rapid Maxillary Expansion) + nasal hygiene; myofunctional exercises |
| 8 – 11 years | Class II (overjet), lower jaw behind upper, deepening overbite | Twin Block or Bionator; most effective during peak pubertal growth spurt |
| 11 – 13 years | Tongue thrust, relapse after earlier treatment | Myofunctional therapy exercises; Trainer appliance; co-managed with speech therapist if needed |
| After 14 years | Growth mostly complete; orthopaedic window has closed | Fixed braces for tooth alignment; surgical consultation for significant skeletal discrepancies |
What Parents Say
“We didn’t know tongue posture was affecting our son’s jaw development until Dr. Mittal’s assessment. Eight months of myofunctional therapy later, his breathing, sleep, and bite are all measurably improved.”
“My daughter had a tongue thrust — she pushed her tongue forward when swallowing. The home exercises were simple enough for a 7-year-old to follow consistently. The therapist was patient and really encouraging.”
“Combined with orthodontics, the myofunctional therapy made the alignment stable long-term. The orthodontist confirmed the results wouldn’t have held without addressing the tongue and lip habits first.”
Frequently Asked Questions
Myofunctional appliances correct jaw position and arch form — but they do not straighten individual teeth. Most children who complete functional orthopaedic treatment will still need a phase of fixed braces to align individual teeth. However, the overall treatment time and complexity of Phase 2 braces is typically significantly reduced by successful early intervention.
There is pressure and a slight pushing sensation after each turn, typically lasting 1–2 hours. This is the palate responding to the expansion force. Paracetamol provides effective relief in the first week. Most children adapt quickly and report little discomfort after the first 5–7 days.
It depends on the severity and cause. Mild skeletal underbites in growing children can be improved with reverse-pull headgear or chin cup combined with upper arch expansion — sometimes avoiding jaw surgery that would otherwise be needed in adulthood. Severe skeletal Class III cases may ultimately require orthognathic surgery after growth is complete.
After the growth window closes, jaw discrepancies can no longer be corrected by growth guidance. The options then are either accepting the discrepancy with camouflage orthodontics (moving teeth to compensate for the jaw mismatch) or correcting the jaw with orthognathic (jaw) surgery after growth is complete. Neither is as simple, as comfortable, or as cost-effective as early intervention.
Braces move teeth into alignment, but if tongue posture, lip strength, or swallowing pattern are abnormal, these muscle forces push teeth out of alignment after the braces are removed. Myofunctional therapy corrects the underlying muscle function, creating a stable oral environment that supports orthodontic results and significantly reduces the risk of relapse. We coordinate the timing of both so they reinforce each other.
Improvement in muscle tone and awareness is typically noticeable within 6 to 8 weeks. Correction of tongue posture at rest and swallowing pattern takes 4 to 6 months of consistent daily practice. Full integration of new muscle habits takes 9 to 12 months. Compliance with the home exercise programme is the single biggest factor in outcome — the exercises are simple but must be done consistently every day.